

DNA sequencing
WGS and WXS data were newly generated for MD Anderson Cancer Center, Duke University Hospital, Henry Ford Hospital, Case Western Reserve University, Chinese University of Hong Kong, Mayo Clinic, Northwestern Medicine, Olivia Newton-John Cancer Research Institute, University of California, San Francisco, Saint Joseph’s Hospital and Medical Center, Seoul National University, and Luxembourg Institute of Health at Jackson Laboratory for Sequencing Medicine genomics. All were subjected to 150 base pair (bp) sequencing using Novaseq (Illumina) according to the manufacturer’s protocol. Longitudinal data previously published by GLASS5.12 and TCGA7 were also used and corresponding sequencing information can be found in previous publications. In total, sequencing data was provided by 21 institutions: Columbia University, University of Florida, German Cancer Research Center, Pitié-Salpêtrière, Samsung Medical Center, Biobank Japan, University of South Wales, University of Sao Paulo, and the 13 aforementioned institutions, including the Jackson laboratory. For the Seoul National University cohort, DNA and RNA were extracted simultaneously from each tumor sample at the Jackson Laboratory for Genomic Medicine using the QIAGEN AllPrep DNA/RNA Mini Kit (80204). For blood samples, DNA extraction was performed using the QIAamp DNA Mini and Blood Mini kits from QIAGEN (51104). A total of 200 ng of DNA was fragmented to 400 bp using an LE220 focused ultrasound machine (Covaris) and then size selected with Ampure XP beads (Beckman Coulter). DNA fragments underwent end repair, A-tailing, and ligation of Illumina Single Adapters (Illumina) using the KAPA Hyper Prep kit from Roche (7962363001). The resulting whole-genome libraries were sequenced with 150-bp paired-end reads on the Illumina NovaSeq 6000. Sequencing coverage averaged 27× and over 100×, respectively, on longitudinal WGS and WXS samples, and driver mutations were consistently supported by sufficient depth (ranging from 30× to 80× for WGS and 80× at 300 × for WXS) in the primary and recurrent phases. tumors, thereby minimizing the effect of coverage variability on mutation detection.
Reference cohorts
GLASS data were compared to data from two reference cohorts: TCGA7 and AACR ENGINEERING (v.18.5)25. Clinical data from patients in the GLASS cohort at baseline were compared to data from TCGA patients with IDH-mutant primary gliomas with respect to age of onset and overall survival.5,7,12. Survival data for patients with oligodendrogliomas and astrocytomas were compared between the GLASS and GENIE cohorts. The GENIE cohort includes primarily panel sequencing data and, in most cases, lacks copy number or coverage data. TERT promoter hotspots. Oligodendrogliomas from the GENIE cohort were therefore defined as IDH mutant gliomas without alteration of TP53 Or ATRXas determined by high-coverage panel sequencing, whereas IDH mutant gliomas with these alterations were termed astrocytomas.
GLASS identifiers
A GLASS barcode system based on the TCGA barcode design was used to identify all samples and their corresponding patients. Briefly, the 24-character barcode includes information about the project, collection center, patient ID, sample type, analyte type, and sequencing platform. Detailed information on barcode distribution is available in a previous GLASS publication12.
IT pipelines
GLASS pipelines for variant and copy number calling were developed using Snakemake (v.5.2.2)46. The Genome Analysis Toolkit 4 (GATK4, v.4.1.0.0)47 suite was used unless otherwise noted. All data were analyzed using homogeneous pipelines capable of processing raw FastQ files.
Alignment and variant calling
Briefly, in terms of alignment and preprocessing, the study adhered to GATK best practices, using various tools to manage and clean binary alignment map files, assign and manage read groups, perform quality control, mark sequencing adapters, align sequences to the b37/hg19 (human_g1k_v37_decoy) genome, merge and mark duplicates, and perform basic recalibration. For variant detection, GATK4 was used, with germline variants called from control samples and somatic variants identified in tumor samples and patient cohorts. Quality control measures included assessing sample cross-contamination and reading for orientation artifacts. As a post-processing variant, BCFTools (v.1.9)48 normalized, sorted, and indexed variants to generate a consensus variant calling format (VCF) file, which was then annotated and used to compare allele frequencies between associated samples, with single-sample variants overlaid on multiple-sample calls to infer mutations from individual samples. Further details on these steps can be found in the previously published GLASS article.5.
Call with copy number
Copy number identification was carried out according to GATK best practices, with different methods for WGS and WXS data. For WGS data, the genome was segmented into 10 kb groups, while overlapping regions from various capture kits were merged for WXS data. Both strategies included counting reads in these bins, subsetting germline variants, and separating the cohort by sequencing center to create a panel of normals. This involved denoising the read counts, annotating intervals for GC content, and inspecting the quality of the results. Call by copy number used a method based on GATK CallCopyRatioSegments and GISTIC (v.2.0.23)26identifying neutral segments and classifying amplifications or deletions based on weighted averages and standard deviations. Chromosome arms were analyzed to set high-level thresholds, and gene-level copy numbers were called by crossing gene boundaries with segment intervals and comparing weighted non-log values.2 copy ratio at these thresholds. These steps have also been described in detail previously5.
Selection of molecular data cohorts
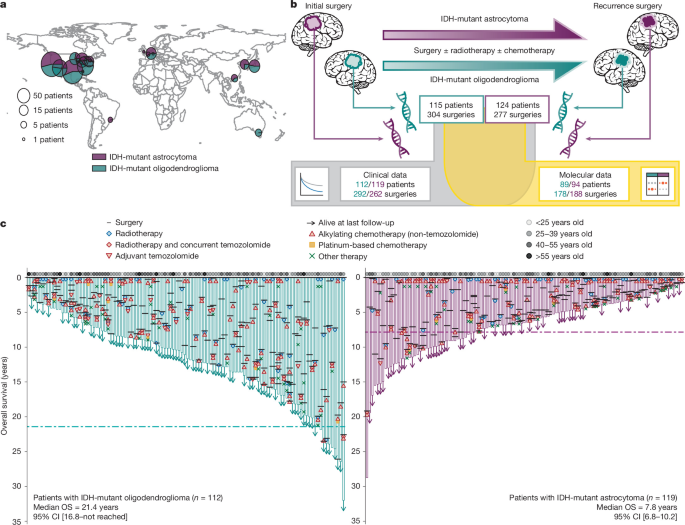
Rigorous quality control measures were implemented to keep surgical procedures spaced in time for molecular analyzes (Extended Data Fig. 1b). The QC criteria required (QC1) that a tumor sample be available and WGS and/or WXS data be generated from the sample; (QC2) that fingerprinting confirmed the identity of the sample using the Picard CrosscheckFingerprints tool49; (QC3) that sequencing coverage was at least 8× for WGS samples and at least 28× for WXS samples, and that the mutation frequency was neither zero nor abnormally high (indicative of FFPE artifacts); (QC4) a minimum interval of 3 months between initial and recurrent surgery; (QC5) the exclusion of patients who have only one surgery remaining and a restriction to two separate surgeries per patient, choosing the first and last surgery available; and (QC6) that copy number profiles met quality thresholds without excessive noise, unexpected genomic stability, or insufficient signal, as independently assessed and jointly reviewed by three of the authors (TC, KCJ, and FSV).
sSNV calling
The dN/dS ratios were estimated using dNdScv (v.0.1.0)50 with default and recommended settings applied to all mutations in initial and recurrent tumor samples, as well as to each mutational fraction (unique to initial, unique to recurrent, and shared). These analyzes were performed separately for each of the two types of IDH mutant gliomas. Adequate sequencing depth and reciprocal mutations between paired samples minimized coverage-related false negatives; Given that our analysis compares shared mutations with sample-specific ones, variation in coverage is unlikely to affect the observed qualitative patterns.
Clonality analysis
We used PyClone-VI51 to assess the clonal status of all sSNVs in our dataset. Briefly, variants with a minimum coverage of 10× in at least one sample from each matched set were included in the analysis. PyClone-VI was run in beta-binomial mode using default settings. Mutations with a cancer cell fraction greater than 0.9 were classified as clonal and those below this threshold were considered subclonal.
GISTICS
GISTICS26 was run on the public version of the GenePattern server, on primary and recurrent tumor segmentation data for each IDH mutant glioma type individually to identify large and focal copy number changes in each group. Analysis was performed using the GeneGISTIC method, with extended event detection and gene collapse values set to the extreme. Additional parameters included a focal length threshold of 0.5 or greater, with a confidence level of 99% and chromosome-arm fit capped at 1.0. Copy number determining genes were identified from GeneGISTIC results.
Aneuploidy calculation
Aneuploidy was calculated at three different levels for all samples: at the arm level, at the segment level, and at the whole genome level. For the calculation of aneuploidy at the arm level, a method described previously was used.52. Briefly, adjacent segments with identical arm-level calls (−1, 0, or 1) were merged, resulting in a single call for each merged segment. The proportion of the chromosome arm covered by each fused segment was calculated. Segments covering more than 80% of the arm were called −1 (loss), 0 (neutral), +1 (gain), or NA, if no segment covered at least 80%. For each sample, the number of arms exhibiting non-neutral events was then counted. As a secondary method, the average log2(copy number ratios) were calculated to compare arm-level aneuploidies between groups. Lower thresholds were set at ±0.1 for significant arm-level gain or loss at any time point and ±0.05 for significant arm-level changes (∆gains or losses).
For the segment-level calculation, each segment was assigned a gain, loss, or neutral status based on the log2 copy rate threshold of ±0.2. Segments with absolute log2 a ratio greater than 0.2 was considered modified. In each sample, the total number of modified segments (gains and losses) was counted.
High-level amplification and homozygous deletion thresholds were determined per sample from segmented copy number data by calculating the weighted mean and standard deviation of the non-log2 copy rate among neutral segments (0.9-1.1), with segment…
Gn Health

