
Medical debt is crushing hospital patients in Los Angeles. Health officials may have a solution: NPR

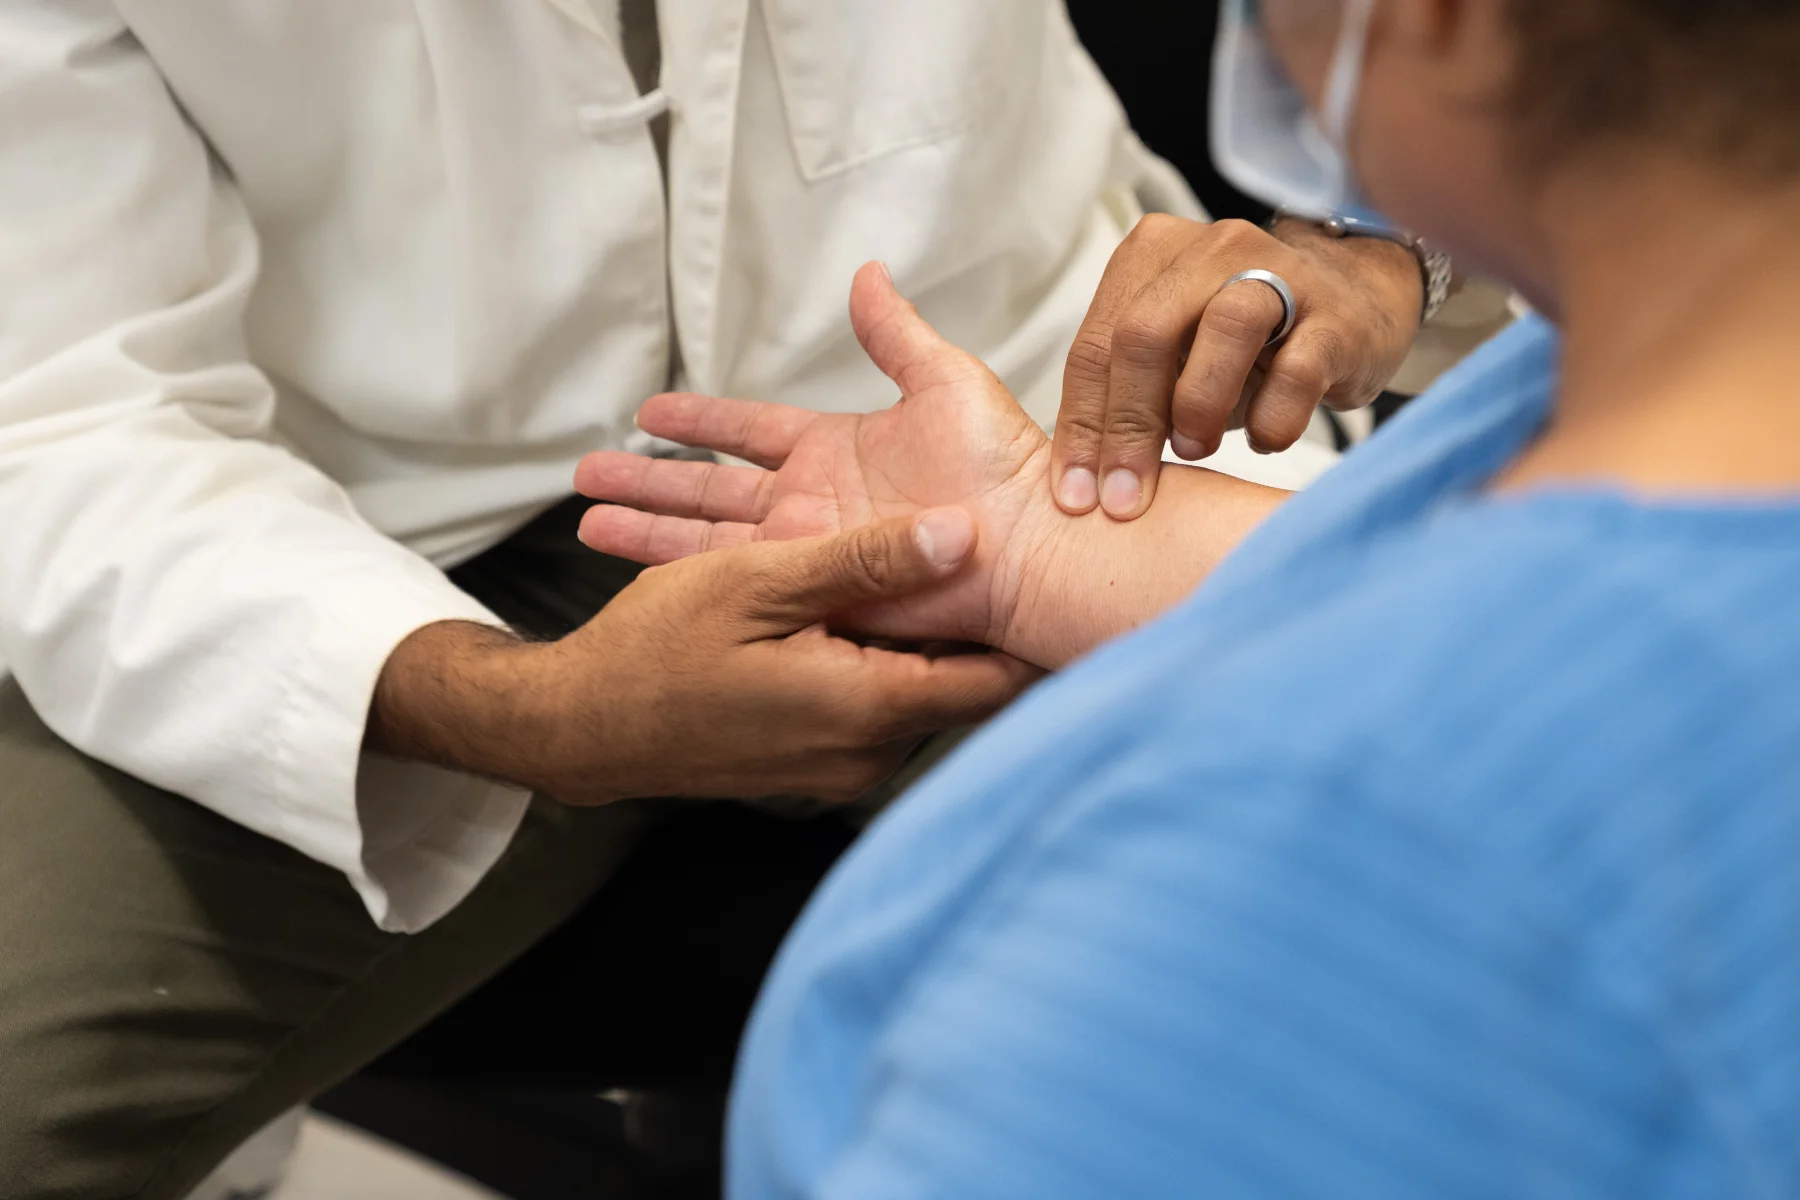
Naman Shah examines a patient at the Monrovia Health Center, a Los Angeles County public health clinic in Monrovia, California. Shah says reducing medical debt in the community will depend on effective prevention strategies, as will stopping the spread of infectious diseases.
Lauren Justice/KFF Health news and compromises
hide caption
Lauren Justice/KFF Health news and compromises
LOS ANGELES — Every Tuesday, Naman Shah sees tuberculosis patients at a small public clinic in Los Angeles’ San Fernando Valley. Shah, a doctor and epidemiologist at the Los Angeles County Department of Public Health, reviews images of bruised lungs, listens for labored breathing and checks medications.
It’s part of an initiative dating back to the early 20th century to control infections so that tuberculosis does not spread. “We like to do things up front,” Shah said, “that is, before they happen, not after the damage is done.”
Now, Shah and his colleagues are applying the same principle to medical debt. A key part of this effort is a new system that allows each LA County hospital to easily screen patients for financial assistance. The goal: to prevent low-income families from being hit with a bill that buries them in debt.
Shah estimates that this system could avoid several hundred million dollars in medical debt each year.
Shah at the Monrovia health center.
Lauren Justice/KFF Health news and compromises
hide caption
Lauren Justice/KFF Health news and compromises
Vicious circle
In the United States, an estimated 100 million adults have some form of health care debt. In Los Angeles County, the nation’s most populous, public health officials estimate that about 800,000 residents have medical bills they cannot afford.

“The impacts of medical debt have been staggering,” said Shah, who worked at a rural health clinic in India and since 2023 has led a Los Angeles County initiative to tackle the debt problem.
“People end up with credit card debt and then into a vicious cycle of high interest rates and poverty,” he said. “People give up on their prescriptions. People give up on their appointments. And then your health deteriorates.”
Hospitals generally offer financial assistance to low-income patients. But information about support is often difficult for patients to obtain. Applying can be tedious. And many eligible patients never seek help, research shows.
“Most people enter and leave the hospital without any knowledge of financial assistance,” said Jared Walker, founder of Dollar For, a nonprofit that helps patients across the country apply for assistance, often called charity care.
“The impacts of medical debt have been staggering,” says Shah, who has led a Los Angeles County initiative since 2023 to tackle the debt problem.
Lauren Justice/KFF Health news and compromises
hide caption
Lauren Justice/KFF Health news and compromises
This fuels the debt. It also leads to costly collection efforts that even hospital officials acknowledge unnecessarily target low-income patients who likely won’t be able to pay.
“They are working to collect debts that are not collectible,” said Adena Tessler, regional vice president of the Southern California Hospital Association.
Presumed Eligibility
One potential solution is a system that automatically screens and qualifies low-income patients for financial assistance without requiring an application. This is called presumptive eligibility.
Some hospitals already use such systems, which rely on software that checks patients’ eligibility based on publicly available information such as credit history.
The strategy can be very effective. Shah said hospitals that have deployed presumptive eligibility systems have reported an increase of up to 50% in the amount of financial assistance they provide to patients.
Under a state law passed last year, all California hospitals will have to begin testing for presumptive eligibility by next July.
But these systems can be expensive and difficult for small hospitals to implement. Only about 1 in 5 hospitals in Los Angeles County currently use them, Shah said.
Public health officials wondered if they could help more hospitals implement these systems.

The county, which like many local governments faces significant budget challenges, can’t pay for it, Shah said. But the public health department could bring together county health care and hospital officials to come up with another solution.
“The beauty of government is not when it always has to get the job done,” Shah said. “We have the ability to ensure that people cooperate.”
The Southern California Hospital Association, initially wary of the county initiative, came to view improved hospital financial assistance programs as beneficial to hospitals, many of which were wasting money on collections. “The billing process is cumbersome and expensive,” said Paul Young, senior vice president of the association.
The association has agreed to adopt a digital system of presumed eligibility and make it available to its members. This bulk-buying approach, which Young likened to “a Costco model,” would reduce costs for individual hospitals, he said.

At the same time, LA Care, a nonprofit health plan that administers Medicaid coverage for more than 2.5 million low-income county residents, committed $2 million to set up the system.
The investment reflects the safety net insurer’s mission to make medical care accessible to more people, said Melanie Fontes Rainer, who leads strategic planning for LA Care. “This is going to improve Los Angeles County,” she said.
Make it work
Getting the new system up and running by January, as partners hope, faces challenges.
Hospital officials are considering how the system will be financed over the long term. And it’s unclear how many of the county’s 88 acute-care hospitals will eventually use it, even though it’s cheaper and easier to access.
The partners are also working to improve the data the system relies on to screen patients. One goal is to link the system to tax records maintained by the state of California. This would provide hospitals with more accurate information about patient income than current systems, which often rely on estimated income.
Walker, the patient advocate at Dollar For, said he is encouraged by the county’s efforts. “I’m optimistic that we can create a better system of charity care,” he said. “And the fact that LA County hospitals are willing to be innovative and creative about ways to do this is extremely encouraging.”
For his part, Shah said county public health officials recognize that a better testing system in hospitals alone will not eliminate medical debt. But he said the public health department can’t ignore an issue that affects more county residents than asthma or smoking.
“Prevention is our livelihood,” he said.
This article is part of Hidden helpa series of investigations Compromise And KFF Health News on how hospitals can protect their patients from the life-altering harms of medical debt.
KFF Health News is a national newsroom that produces in-depth journalism on health issues and is one of the major operating programs of KFF — the independent source for health policy research, polling and journalism.
Gn headline


