
Population-wide reconstruction of menopause dynamics reveals physiological cliff during last menstrual period

Ethics approval
This study complies with all relevant ethical regulations. The use of the Clalit Health Services dataset was approved by the Clalit Helsinki Committee (RMC-1059-20). We used public NHANES data that was conducted with approval from the Research Ethics Review Board of the National Center for Health Statistics. The current study analyzed existing anonymized data and participants received no compensation from the investigators. Gender was considered in the study design because menopause is a biological process specific to women, with men included as comparison controls. Sex was recorded by the source datasets (self-reported in NHANES and recorded in the Clalit electronic medical record); gender identity was not available.
Data and cohorts
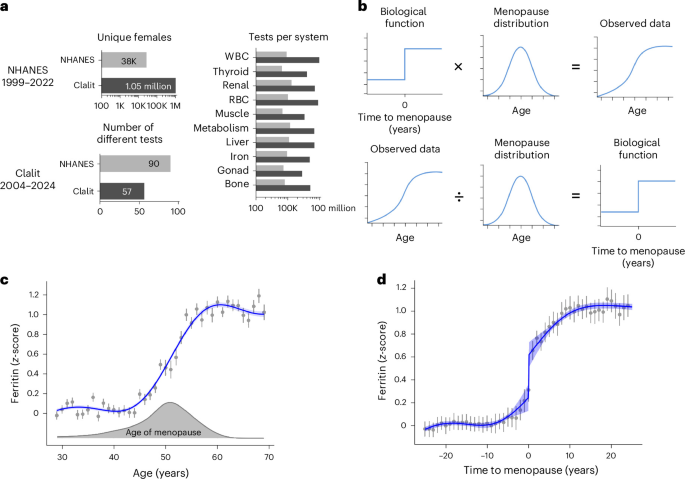
We analyzed two datasets from the United States (NHANES) and Israel (Clalit). NHANES is a cross-sectional health study that was collected every 2 years from 1999 to 2022 and includes laboratory tests, health questions, examinations, and outcomes.35. Clalit is a large longitudinal electronic health record dataset (all comers) that includes approximately half of the Israeli population.15. We analyzed healthy laboratory test data that excluded data points with confounding drug or disease effects.15which gives 1.3 million eligible women aged 30 to 70 between 2004 and 2024.
Eligibility Criteria
Clalite
We analyzed all arrivals aged 30 to 70 years between 2004 and 2024. We excluded pregnant women (N = 173,000).
NHANES
We analyzed 12 biennial waves from 1999 to 2022. We excluded pregnant women (N = 1,326). For the MHT comparison (Fig. 3), we analyzed only women from survey years 1999 to 2019 (2022 had no MHT data due to coronavirus disease 2019 (COVID-19)), with all covariates necessary for matching: menopause status, age, poverty income rate, smoking status, insurance status, diabetes status, ethnicity, and education, with the outcome final. N = 738 MHT users.
Variable definitions
Menopausal status (NHANES only)
We included all non-pregnant women, regardless of the reason for menopause (in the sensitivity analysis we limited ourselves to natural menopause at typical ages, showing results very concordant with those of Pearson). r= 0.97; Supplementary Figure 7). Menopausal status (women only) was determined using the clinical definition of 12 months without periods.2 as well as additional information to confirm the status. We used two questions, the first is: have you “had regular periods/at least one in the last 12 months?” The second follow-up question is “what is the reason (absence of periods)?” ”, where we ask the individual to specify “menopause” as the reason. Individuals reporting periods were defined as non-menopausal (RHQ030/RHQ031, regular periods/at least one period in the past 12 months). Individuals were further classified as follows. People reporting not having periods were classified as non-menopausal if they reported being pregnant (this year or before) or breastfeeding, while people self-reported as menopausal were classified as postmenopausal (RHQ040/RHD042/RHD043, reason for not having regular periods); people who reported another reason for not having a period were classified as having unknown menopausal status (NA, not available). RHD042 did not differentiate menopause from hysterectomy as the reason for lack of regular periods, but these cases were subsequently corrected as follows. We reclassified all women who had a hysterectomy and reported having only one or no ovaries removed as age and menopausal status unknown (NA), because hysterectomy would prevent them from menstruating (RHQ300/RHQ305/RHQ310/RHQ320); women who reported their age at menopause before their age at hysterectomy (RHQ291) were still included. We included participants taking oral contraceptives. Some of these people may not have periods, in which case they were classified as having unknown menopausal status. Finally, some people with undetermined menopausal status were classified by age as follows: non-responders with regular periods (RHQ030/RHQ031) under 30 years of age were classified as non-menopausal, and responders over 60 years of age who reported not having regular periods were classified as menopausal (justified by the observed statistics which showed that 98.3% of women are not menopausal at age 30 and only 0.9% of women were not menopausal at age 60). Self-reported age of menopause is top-coded at 60 years in NHANES, which was extrapolated using a survival model.36 as described in the “YoGlen 1 method for NHANES data” section. Clalit did not have menstrual data, so menstrual status was not used for this dataset. Men and the 26.8% of women with unknown menopausal status were assigned a menopausal age using the YoGlen algorithm described later in the methods section. We performed a sensitivity analysis to account for the effects of unknown menopause status, hysterectomy and early/late menopause in Supplementary Figure 7, which shows almost perfect agreement of results, r= 0.97, between a restricted age range of 45–53 years with known menopausal status and our reported FMP jump sizes.
MHT
NHANES
We considered women to be currently taking MHT if they had a known postmenopausal status and if (1) they reported taking MHT or (2) reported taking estrogen-containing medications (full list in Supplementary Table 3). For (1), we controlled for NHANES using the RHQ540 (ever using female hormones excluding birth control): any participant reporting “no” was classified as non-MHT. Answering yes to any of the following was classified as yes MHT: RHQ558 (currently taking estrogen-only pills; 2.9% of women), RHQ566 (currently taking progestin-only pills; 0.2% of women), or RHQ574 (currently taking a combined pill; 1.1% of women). After 2012, NHANES stopped asking specific questions regarding MHT use. For (2), we used the RQQ_RX prescription drug files from each year except 2022 (not reported). We included the following types of estrogen-containing drug classes as MHT: all “E2,” estropipate, mestranol, all “estrogens,” as well as nine individuals using progesterone-only MHT.
Clalite
In Clalit, menopausal status is not recorded. We therefore defined MHT users as women aged 45–55 years who were prescribed at least twice the MHT medications Angeliq (drospirenone 2 mg – estradiol hemihydrate 1 mg) or Eviana (estradiol hemihydrate 0.5 mg – norethisterone acetate 0.1 mg). We compared these individual users with controls from the same clinic, same age, and same year of birth. For each laboratory test and each group, we defined menopausal change Δ as the mean of the postmenopausal window (54 to 60 years) minus the corresponding mean in the premenopausal window (42 to 48 years). ΔMHT is the mean menopause change for MHT patients, and Δcontrol is the mean menopause change for the control group. MHT attenuation is defined as the relative reduction in menopausal change of MHT users compared to their matched controls: 1 − (ΔMHT/Δcontrol).
Variables and results
We analyzed 90 laboratory blood tests and 31 results to determine their time dependence on the time inferred from the FMP. We group by systems as described in Extended Data Table 1 and Supplementary Table 2. Blood tests describe bone, liver, kidney, immune, and other systems. Results include signs, symptoms and diagnoses.
Pretreatment
Clalit and NHANES
All laboratory values were logarithmically scaled and standardized to the sex-specific mean and standard deviation, using the control reference age range of 25–45 years (data sets were standardized separately). An outlier threshold was applied at ±5 sd (<0.3% of data points). The distributions of log laboratory values resembled normal distributions.
Clalite
Lab values were filtered to exclude measurements from unhealthy individuals and people taking medications that affect each specific lab test. To do this, we used the dataset described by Cohen et al.15which excluded 131 chronic diseases and 5,223 drug-test pairs. Pregnancies were excluded separately. Body mass index (BMI) was linked cross-sectionally for the healthy population using the most recent measurement during the study period and reported as median (IQR). Bootstrapping on Clalit was carried out by grouping individuals by year of test date and sampling the 20 years with replacement. Test values of zero were removed (<0.3% of data points; extended data table 2).
The YoGlen algorithm
We estimate the unknown age of the FMP using a latent variable model37 with appropriate approximations. To leave pdenotes an arbitrary probability density function, Am is the unknown age of the FMP, mis the binary variable of menopause status (available in NHANES but not in Clalit), Ais the known age, and Yes is a vector of known laboratory test values. The two results we obtain are (1) how to estimate the distribution of the unknown age of the FMP of each individual, \(p({a}_{m}|{\bf{y}},a)\) using the observed data and (2) how to estimate the laboratory average transverse trajectories as a function of the unknown time to the FMP, \(E({y}_{j}{|a})\). The jump size was estimated using the predictions from the resampled regression model. For method 1, we used ten-fold cross-validation. For method 2, we used the bootstrap of \(E({y}_{j}{|a})\).
YoGlen 1 method for NHANES data
To estimate the unknown FMP time, \(p({a}_{m}|{\bf{y}},a)\) we use Bayes theorem \(p({a}_{m}|{\bf{y}},a,m)\propto p({a}_{m}{|a},m)p({\bf{y}}|{a}_{m},a,m)\). We observed, based on a comparison with SWAN data (Extended Data Fig. 5), that a good approximation was to use only the lowest order term. \(p({a}_{m}|{\bf{y}},a,m)\approx p({a}_{m}{|a},m)\). We used prints of \(p({a}_{m}{|a},m)\) impute the unknown AmOr p(Am) is the reference age distribution of menopause from NHANES (Fig. 1), estimated by modeling the log-risk as a ten-knot natural spline.36. Women who underwent double oophorectomy (12%) were selected separately using their own distribution. For women where…
Gn Health


