
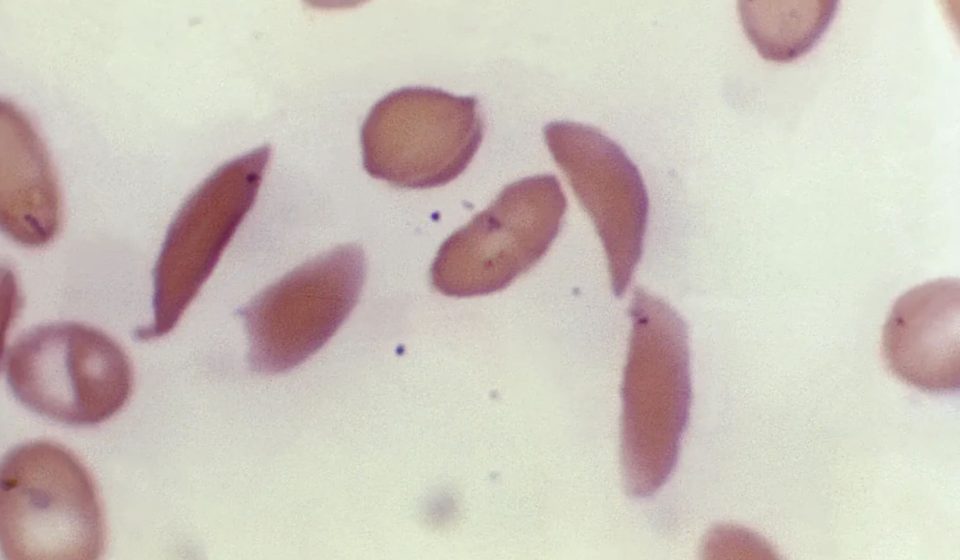

This microscope photo provided Oct. 25, 2023, by the Centers for Disease Control and Prevention shows crescent-shaped red blood cells from a patient with sickle cell disease in 1972. Britain’s drug regulator has approved the world’s first gene therapy treatment for sickle cell disease, a move that could bring relief to thousands of people with the crippling disease in the United Kingdom.
Dr. F. Gilbert/CDC via AP, file
For decades, people with sickle cell disease have endured lifelong hospital visits, medications and blood transfusions to manage a painful genetic blood disorder that can reduce life expectancy by up to 20 years.
But a long-awaited breakthrough came in 2023, when the US Food and Drug Administration approved Casgevy and Lyfgenia, the first two gene therapies for patients with severe forms of the disease. Patient advocates and clinicians say recent advances in treatment could mark the start of a new era in sickle cell care, one that could free thousands of people from recurring episodes of debilitating pain and improve long-term health outcomes.
“This opens the door to a whole world of individuals potentially being cured of sickle cell disease,” said Dr. Edward Donnell Ivy, chief medical officer of the national patient advocacy organization Sickle Cell Disease Association of America.
Yet for thousands of people living with the disease, accessing transformative therapies remains far from simple.
Patients often face a fragmented and uneven healthcare landscape where treatment costs, a complex treatment process, provider availability, and access to specialized treatment centers can vary significantly depending on where they live. The result left therapies that could radically alter the course of the disease still out of reach for many eligible patients.
“Patient priorities actually play a big role in determining barriers to access and how to overcome them,” said Dr. Alexis Thompson, an attending physician in the division of hematology at Children’s Hospital of Philadelphia and a spokesperson for the American Society of Hematology.
Path to a breakthrough
Sometimes called the “most common rare disease” because millions of people worldwide are affected, sickle cell disease affects about 100,000 people in the United States, according to the Centers for Disease Control and Prevention. More than 90% of the patient population is non-Hispanic Black or African American.
Sickle cell disease is a genetic blood disorder that causes normally flexible, round red blood cells to become stiff and crescent-shaped, which can block blood vessels and reduce oxygen delivery to tissues.
Some of the most common health complications that can occur include chronic fatigue and anemia, as well as blood clots and what are called vaso-occlusive or “pain” crises, which are severe episodes of debilitating pain that can last from a few hours to several weeks. Other complications may include stroke, organ damage, and increased risk of infection.
…from 1910 until approximately 2015, there was very little progress in disease-modifying treatments for sickle cell disease.”
Dr Andrew Campbell
National Director of the Children’s Sickle Cell Program
More than a century after the first documented case of sickle cell disease in the United States in 1910, progress in developing new treatments has remained slow, in part because of decades of underinvestment and lower levels of philanthropic support than received for other rare genetic diseases. From 2008 to 2018, National Institutes of Health research funding for sickle cell disease averaged $812 per patient, according to a 2020 analysis. In comparison, funding for the genetic disease cystic fibrosis, which affects about 40,000 people in the United States, averaged $2,807 per patient for the same period.
“There has been a slow increase in the development of new treatments for sickle cell disease,” said Dr. Andrew Campbell, director of the Comprehensive Sickle Cell Program at Children’s National in Washington, DC. “In the last six or seven years there has been an explosion, but I would say from 1910 until about 2015 there was very little progress in disease-modifying treatments for sickle cell disease.”
A major breakthrough came in 1998 with the FDA’s approval of hydroxyurea, the first drug shown to modify the health effects of sickle cell disease. Studies have shown that the drug helped reduce the frequency of pain attacks in patients by half, as well as the need for hospitalizations and blood transfusions. Since its introduction, hydroxyurea has become the cornerstone of treatment for sickle cell disease and has helped thousands of people successfully manage their disease.
Signage is seen outside the U.S. Food and Drug Administration headquarters in White Oak, Maryland, August 29, 2020.
Andrew Kelly | Reuters
Yet the discovery of a cure remained elusive until gene therapy. For years, the only option available to patients was to undergo a bone marrow transplant, which was limited to a select number of people able to find a compatible donor.
“Bone marrow transplant has always been available, but it was not a good option because few people had access to a donor,” said Ivy, who also has sickle cell disease. “Now that we have cell and gene therapies, an individual can act as their own donor.”
Slow patient care
Gene therapy has been shown to achieve a high efficacy rate, with 88-94% of patients being completely free of severe vaso-occlusive crisis.
Yet despite their curative potential, adoption of gene therapies for sickle cell disease has been slow. By the end of 2025, a total of 64 patients worldwide had received Casgevy infusions, according to an annual results report from manufacturer Vertex Pharmaceuticals, while another 147 people had undergone their first cell collection for the treatment. Lyfgenia’s maker, Genetix Biotherapeutics, reported that 115 U.S. patients have been treated with the gene therapy since its approval in 2023, and another 216 began cell collection by the end of 2025.
Gene therapy can be a daunting process that may deter some patients. This requires collecting the patient’s hematopoietic stem cells and modifying them so that they produce healthy hemoglobin, then returning those cells to the patient’s body. Patients go through a condition stage before receiving the cells where they receive chemotherapy, blood transfusions and undergo frequent hospital stays that can last weeks.
The entire therapy can take up to a year, with the conditioning process often causing permanent infertility or sterility.
Currently, patients as young as 2 years old with sickle cell disease can receive Casgevy, while Lygfenia is available to patients 12 years and older. Both therapies are approved for patients with severe forms of the disease, such as those with genotypes such as HbSS, which comprises a majority of patients, or HbS beta “zero” thalassemia. Likely candidates include patients who have experienced at least four painful attacks or episodes of acute chest syndrome in the 24 months before treatment. Studies have estimated that between 25% and 35% of the patient population would meet current clinical criteria for gene therapy.
Ivy remembers experiencing four to five pain attacks a year that required her to be hospitalized each time before she started taking hydroxyurea for a research study. He said the drug dramatically changed his life, allowing him to complete his medical studies without episodes of pain.
However, when it came to gene therapy, Ivy said he chose to forgo this treatment due to the demands placed on his body and his time. “If I was younger, I would seriously consider it, for sure,” Ivy said. “But there are many things to consider.”
Physical demands aside, the cost of gene therapy could potentially prevent more sickle cell patients from seeking treatment. The list price for a single treatment ranges from $2.2 million to $3.1 million. This cost does not include healthcare expenses such as hospital stays, chemotherapy, or necessary specialized care.
But efforts have been made to address potential cost disparities between patients with private health insurance and the majority of sickle cell patients with health coverage through Medicaid or the Children’s Health Insurance Program, according to Dr. Alexis Thompson, an attending physician at Children’s Hospital of Philadelphia and a spokesperson for the American Society of Hematology.
One of the largest efforts began in 2024 by the Centers for Medicare and Medicaid Services. The Cell and Gene Therapy Access Model is a program under which the agency enters into agreements with states and manufacturers to set prices for gene therapy care based on patient outcomes, with the goal of reducing costs associated with the therapy itself and supportive care. Currently, 32 states, the District of Columbia, and Puerto Rico participate in the CMS model.
Thompson acknowledged, however, that the type of services covered by the program can vary. “Depending on the state a person is in, some coverages may be more comprehensive than others,” she said.
Although Medicaid covers the cost of gene therapy for sickle cell disease, questions remain about how health care providers manage the high upfront costs of treatment as reimbursement remains complex and continues to evolve. Such costs can create financial challenges for hospitals and health systems before reimbursement is finalized.
Although cost is a concern, access to gene therapy may not be as difficult as finding a qualified health care provider who can provide the treatment. Hospitals need a multidisciplinary team of specialists working together to provide care to patients before, during and after treatment.
…there is a gap between the number of patients and…
Gn Health


