
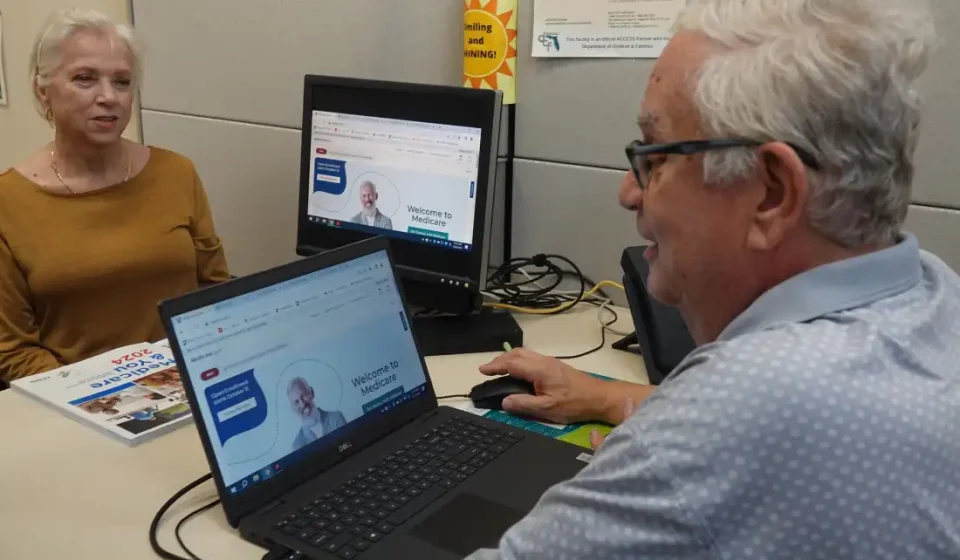

A counselor, right, helps a client through the Medicare enrollment process at a senior resource center in Sunrise, Florida. The Medicare open enrollment season began October 15 and ends December 7.
Joe Cavaretta/South Florida Sun Sentinel/Tribune News Service via Getty Images
hide caption
Joe Cavaretta/South Florida Sun Sentinel/Tribune News Service via Getty Images
Annual open enrollment is underway for Medicare, the federal program that provides health insurance to about 70 million people. Coverage choices are complex and often consequential.
Open registration runs until December 7. The plan you choose takes effect January 1 for the entire calendar year.

Create your own Medicare menu
Medicare provides health insurance to people 65 or older, as well as some younger people with disabilities or certain health conditions. But it’s not just one plan. It’s more of a menu for creating your own insurance.
About half of beneficiaries are enrolled in traditional Medicare, which includes Parts A and B. Administered by the federal government, the plan covers hospital stays, skilled nursing care, doctor visits, outpatient care and preventative screenings. Enrollees can generally see any health care provider that accepts Medicare, and they rarely need approval for diagnostic tests, such as MRIs and CT scans. However, there is no cap on out-of-pocket costs in traditional Medicare, and it does not cover most dental, vision, or hearing prescriptions or services.
As a result, most traditional Medicare enrollees purchase additional coverage from private insurance companies under Medicare Part D, the prescription drug plan. Some also purchase a Medigap policy that covers costs that traditional Medicare leaves behind, such as deductibles, copays and coinsurance.
Health Insurance Advantage
This year, the other half of Medicare beneficiaries opted for privately offered all-in-one managed care plans, known as Medicare Advantage, typically including coverage for prescription drugs, dental and vision. The disadvantages are smaller networks and a greater likelihood that treatments and medications will require prior authorization. Like traditional Medicare beneficiaries, Medicare Advantage participants also pay Part B premiums.
“People really need to do their research before signing up for Medicare, because there are tradeoffs,” said David Lipschutz, co-director of the Center for Medicare Advocacy.
Hassle Saves Money
Each fall, insurers that offer Part D and Advantage plans send enrollees a vital document called an annual notice of change. This is a checklist describing what will be different the following year: premiums, deductibles, covered medications. Consumer advocates and Medicare experts say people sometimes make the costly mistake of throwing it away or filing it away without reading it. Can’t find it? Call the insurer and ask for another copy.
The Centers for Medicare & Medicaid Services projects that the average Part D premium will increase by less than $1 per month for a stand-alone prescription drug plan, describing the market as stable. But this average doesn’t tell the whole story. An analysis from KFF, the nonprofit health policy research organization that includes KFF Health News, found that enrollees who remain in their prescription drug plan will see a 50% increase on average, from $34 to $51. About 10.4 million people could pay higher premiums, not including higher deductibles and coinsurance costs.

About 4 million people are in Medicare Advantage plans that won’t be offered in 2027. If they do nothing, they will be automatically enrolled in traditional Medicare.
Jenny Kane/AP
hide caption
Jenny Kane/AP
Some beneficiaries who have not had to pay monthly premiums in recent years will begin paying for Part D prescription drug coverage in 2027. While this change follows the 2025 introduction of federal caps on out-of-pocket drug spending, it comes as the Trump administration is ending temporary federal subsidies that have helped keep premiums low. The out-of-pocket limit for prescription drugs in 2027 will be $2,400, a total amount that enrollees can choose to distribute over the course of the year.
Juliette Cubanski, who directs the health insurance policy program at KFF, said people who don’t shop around could be leaving money on the table.
“It’s worth avoiding any unpleasant surprises in the form of higher premiums or higher cost sharing for covered services in 2027,” she said.
Some packages are no longer offered
An estimated 4.3 million people now have to search for a new Medicare Advantage plan or prescription drug plan after private insurers left the market. Those who wish to remain in Medicare Advantage must select new coverage or they will automatically be transferred to traditional Medicare. For those looking for a new plan, low monthly premiums can be attractive, but it’s important to read the fine print and add up the other costs.
“There will often be increases in cost sharing and copayments, increases in out-of-pocket limits, and reductions in the scope of some of the additional benefits offered by Medicare Advantage plans,” Lipschutz said.
So ask: Is my prescription covered? Is my pharmacy preferred? Is my doctor in network? What does the dental benefit actually cover?
And pay attention to the maximum amount you have to pay for Advantage plans, Cubanski said, so you know how much you may have to pay out-of-pocket in 2027.
“Look specifically at that dollar value,” she said.
For those switching to traditional Medicare, it will not come with a drug plan, so enrollees must enroll in a new Part D plan if they want most prescriptions covered. Enrollees who miss this step when first eligible may not receive drug coverage for the upcoming year and may be assessed a late enrollment penalty on their monthly premiums for life.
When selecting a drug plan, enrollees must also tell their insurer how they want to pay, either by receiving a bill in the mail or having the cost deducted from their Social Security. If you do not choose a payment plan, you may be excluded from coverage.

If enrollees choose to switch from their Medicare Advantage plans to traditional Medicare during their first year of Medicare, they have the guaranteed right to purchase a Medigap plan, without a health exam. After that, all bets are off: Insurers in most states can deny enrollment or charge more because of a health issue. Exceptions are Connecticut, Maine, Massachusetts and New York.
Enrollees whose Advantage plans have not been renewed – and have not been consolidated into another plan – can switch to traditional Medicare and purchase a Medigap policy without a health exam, but they must act before March.
For help with your purchases, consider “SHIP.”
Medicare experts advise enrollees to write down all their prescription medications, as well as any procedures planned within the next year, such as joint replacement or dental work, to help them decide which plan will cover their needs. Call a preferred doctor’s office to see if they are in network for the plans being considered. Please keep in mind that brokers may earn commissions, particularly on Advantage plans, and may not represent all plans.
For unbiased help, every state has a federally funded Health Insurance Assistance Program that offers free diet advice specific to your situation, in person and over the phone. For assistance, go to the website at shiphelp.org/open-enrollment, email info@shiphelp.org, or call the SHIP National Technical Assistance Center at 877-839-2675.
A SHIP counselor can also help enrollees apply for benefits that help pay Medicare premiums and prescription drug costs, such as Medicare Savings Programs and Medicare Part D Extra Help.
KFF Health News is a national newsroom that produces in-depth journalism on health issues and is one of the major operating programs of KFF — the independent source for health policy research, polling and journalism.
Gn headline


